
Can you get rid of hip dips? No. Not with exercise, diet or any program, and anyone who promises it is guessing. Hip dips come from the shape of your bones, and training does not move bone. What training can change is the muscle and fat around them, and that changes how your hips and butt look. Here is what research has measured, what it has not, and what we would do if hip dips bother you.
Define: Hip dips
The inward curve on the side of your hips, between the top of your pelvis and the top of your thigh bone. Also called violin hips. The medical name is trochanteric depression (Lourenco 2024). They are normal anatomy, not a defect or a sign of poor training.
What causes hip dips?
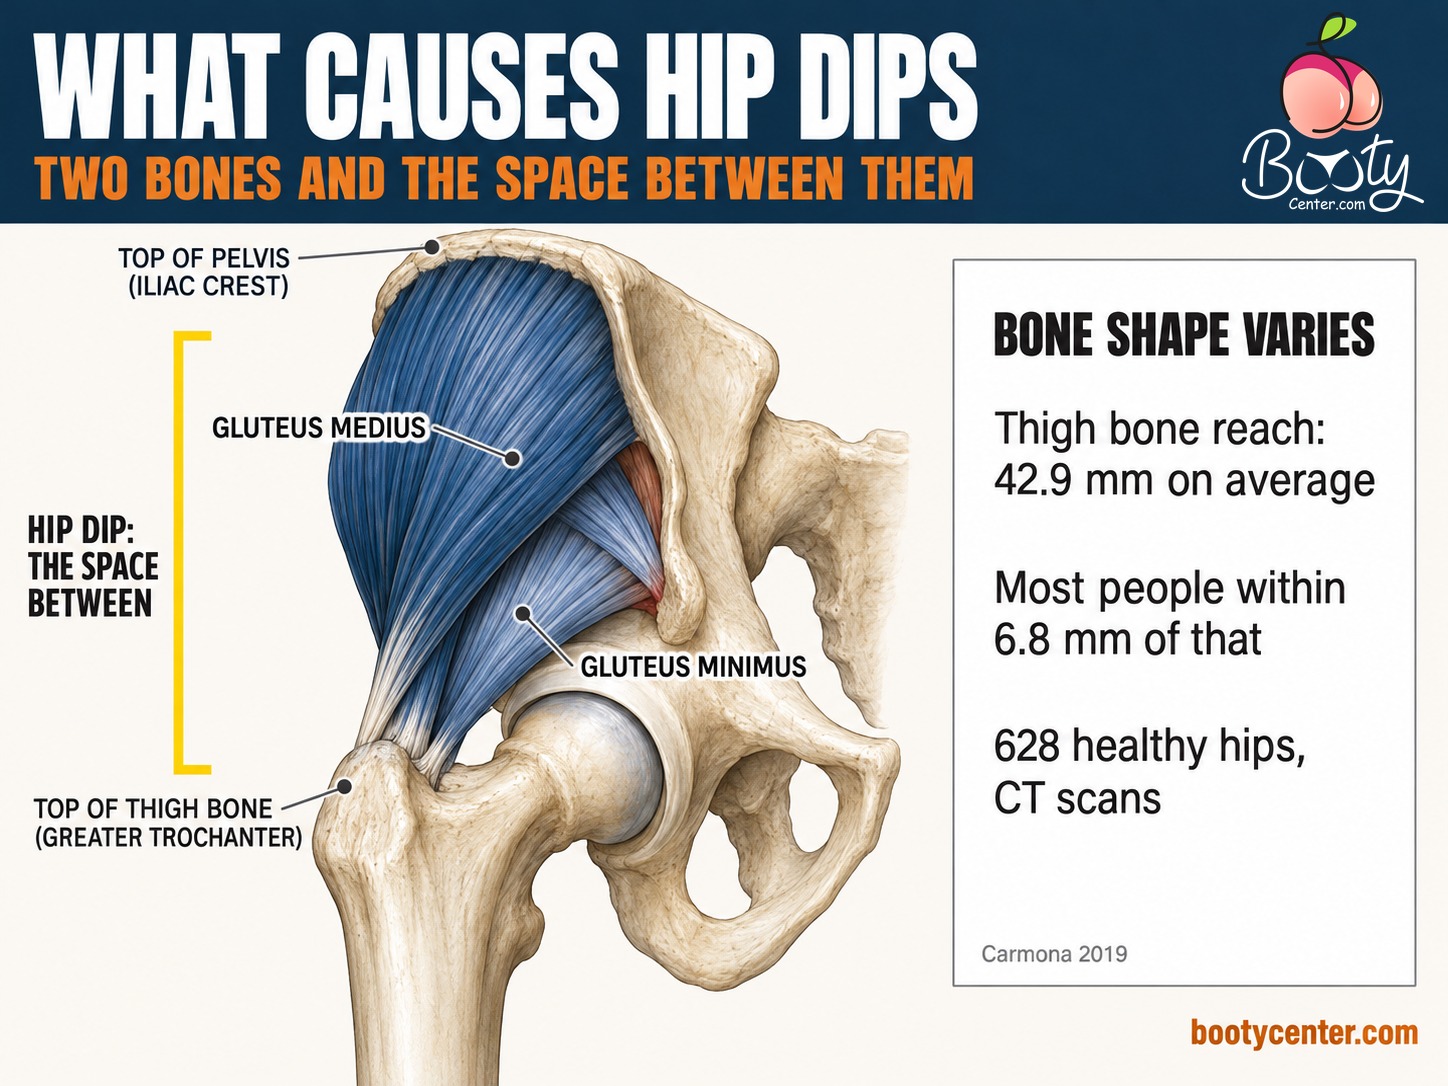
Two bones. Put your hands on your hips: the ridge you feel is the top of your pelvis, the iliac crest. Lower down and further out is a bony bump at the top of your thigh bone, the greater trochanter. A hip dip is the space between those two points. Only muscle, fat and skin cover it.
How deep the dip looks depends on how wide your pelvis is, how long and angled the neck of your thigh bone is, and how muscle and fat sit over the gap. Bone shape varies a lot. In CT scans of 628 healthy hips, the sideways reach of the thigh bone, called femoral offset, averaged 42.9 mm, and most people sat within 6.8 mm of that. The angle of the thigh bone neck averaged 124.7 degrees, give or take 6.2 degrees, and women's hips differed from men's (Carmona 2019). That is why two women with the same training and the same body fat can have very different hips.
Over the gap sit three layers: the side glutes (gluteus medius and gluteus minimus) on the bone, then fat, then skin. Bone does not change with training. Only the muscle and fat layers can.
Can you get rid of hip dips with exercise?
No. Exercise cannot move your pelvis or your thigh bone, so it cannot remove the dip. It can change the muscle around the dip. Whether that makes the dip look smaller has never been measured in any study.
The usual advice, side leg raises, clamshells and squats to fill the dip, rests on one idea. Gluteus medius sits right over the dip, so growing it should fill the gap. It is the biggest muscle on the side of the hip, about 60% of the cross-sectional area of the hip abductors, the muscles that lift your leg out to the side (Neumann 2010). The idea makes sense. It has just never been tested. Size and shape of these muscles also vary a lot from person to person (Flack 2012), so even a good result in one person would not predict yours.
Can you fill hip dips naturally?
Filling hip dips naturally usually means growing the side glutes. Three studies have measured side glute size with MRI before and after training. None found the growth the usual advice promises:
- 9 weeks, 34 untrained adults, squats or hip thrusts. Gluteus maximus grew in all regions with both exercises. Gluteus medius and minimus showed little to no growth (Plotkin 2023). The side glutes were measured on a single scan slice and grouped together, so small changes could be missed.
- 12 weeks, people with hip arthritis, targeted glute program. Gluteus minimus grew a small amount, 0.06 cm3 per kg of body weight more than a fake program. Gluteus medius did not change (Rostron 2022). These were patients, not healthy gym-goers.
- 36 weeks, 12 inactive women, Pilates twice a week. No change in any glute muscle (Dorado 2020). A small group and light loads.
What is missing matters most. No trial has tested heavy, progressive hip abduction for side glute growth in healthy people. That is a gap in the research, not proof that it cannot work.
What are the best exercises for hip dips?
No exercise is proven to change hip dips, so best here means best bet. Hip abduction, lifting the leg out to the side against resistance, is the only common movement that trains gluteus medius through its main job. In 21 active adults, side-lying hip abduction produced the highest gluteus medius activity of 12 exercises, 81% of maximum, against about 40% for clamshells, 48% for lunges and 64% for the single-leg squat (Distefano 2009).
High activity during an exercise does not prove the muscle will grow. In arm muscles, the parts most active during training grew the most over 12 weeks (Wakahara 2013). That has not been tested in the glutes. Treat it as a reason to try, not a promise.
 A coach's template, 2 times a week. The best bet, not a proven hip dip fix.
Here is the plan we would use. It is a coach's template built on the studies above, not a tested hip dip program. Do it 2 times a week, with at least 48 hours between sessions:
- Seated hip abduction machine: 3 sets of 12 to 20 reps, stopping 1 to 2 reps before failure (8 to 9 out of 10 effort). Rest 90 seconds. When you reach 20 reps on every set, add weight. Our guide to seated hip abduction machine form covers the set-up.
- Side-lying hip abduction with an ankle weight, or standing cable abduction: 2 sets of 15 to 20 reps per side, 8 out of 10 effort. Rest 60 seconds between sides.
- Hip thrust: 3 to 4 sets of 6 to 12 reps, stopping 2 reps before failure (8 out of 10 effort). Rest 2 to 3 minutes. This one is for gluteus maximus, the part of your butt that reliably grows. See how to do a barbell hip thrust.
- Bulgarian split squat or single-leg Romanian deadlift: 3 sets of 8 to 12 reps per leg, 8 out of 10 effort. Rest 90 seconds between legs. The single-leg squat and single-leg deadlift worked both the side glutes and gluteus maximus (Distefano 2009). See our guide to Bulgarian split squats for glutes.
Coach's tip
Judge abduction work by the weight on the machine over months, not by the mirror. If the weight keeps going up, you are giving the muscle the best chance it has.
What does training change?
Gluteus maximus growth is the solid part. A 2025 review of 11 studies found a clear, moderate effect of resistance training on gluteus maximus size (Krause Neto 2025). In the 9-week study, the upper part of gluteus maximus grew too (Plotkin 2023). That part sits above and behind the dip, and in a 2025 imaging study its fibres also appeared to help lift the leg out to the side (Takahashi 2025).
 Only one of the four layers reliably responds to training: gluteus maximus (Krause Neto 2025).
So training changes the shape around the dip: a bigger, rounder butt and a fuller upper glute. It does not change the dip itself. For the full picture of how to grow your glutes, see our guide on how to train glutes.
Does losing weight make hip dips go away?
Usually not, and it can make them look deeper. In women, fat on the hips and thighs is one of the clearest sex differences in where the body stores fat (Karastergiou 2012). It works as a long-term store and is less active than belly fat (Manolopoulos 2010), so it tends to be slow to shrink. You also cannot choose where you lose fat from. When the fat layer over the hips gets thinner, the bone shape underneath shows more clearly. That last point is anatomy reasoning, not a measured result.
Are hip dips bad or a sign of weak glutes?
No. No study links hip dips to weak glutes, poor health or injury risk. They are bone shape. Plenty of strong, lean lifters have visible hip dips, which is a coach's observation, not data. Fat stored on the hips and thighs is actually linked to better metabolic health than fat stored on the belly (Manolopoulos 2010). If you want to know whether your glutes are weak, check the real signs in our guide on signs of weak glutes.
What about fillers and surgery?
Doctors can add volume to the area with fillers or fat transfer. The only peer-reviewed paper we found that uses the term hip dips describes a hyaluronic acid filler technique in 11 women, with no comparison group (Lourenco 2024). That is a technique report, not proof of safety or lasting results. This is a medical decision. Talk to a board-certified dermatologist or plastic surgeon, not a coach.
How do you know your training is working?
Bone sets the dip, so do not judge your training by it. Track these instead:
- Your hip thrust numbers. Weight and reps going up over 8 to 12 weeks means gluteus maximus is getting the signal to grow.
- Your abduction machine weight. Write it down every session. Progressive load is the one input that would matter for the side glutes.
- A level pelvis on one leg. Stand on one leg for 30 seconds in front of a mirror. If your opposite hip stays level, your side glutes are doing their job.
- Photos every 4 weeks, not every week. Same light, same time of day, same clothes. Weekly photos show noise, not change.
Hip dips, by the numbers
- 0: trials that have tested heavy hip abduction training for side glute growth in healthy people.
- 628 hips: CT scans showing how much thigh bone shape varies between people and between sexes (Carmona 2019).
- About 60%: gluteus medius share of the hip abductor muscles (Neumann 2010).
- Little to no growth: side glutes after 9 weeks of squats or hip thrusts, in 34 untrained adults (Plotkin 2023).
- 81%: gluteus medius activity in side-lying hip abduction, the highest of 12 exercises tested (Distefano 2009).
- 11 studies: in the 2025 review showing resistance training reliably grows gluteus maximus (Krause Neto 2025).
Where the evidence runs thin
No study has measured hip dips themselves, before and after training. The side glute studies used single scan slices, patients with hip arthritis, or light Pilates, not heavy abduction in healthy people. The link between muscle activity and growth comes from arm muscles. The weight loss point and the observation about lean lifters are reasoning, not data. The training plan is a coach's template. We will update this page when a real trial appears.
Bottom line
You cannot get rid of hip dips. They are the space between two bones, and training does not move bone. Training reliably grows gluteus maximus, which changes the shape of your butt around the dip. Heavy hip abduction is the best untested bet for the side glutes. Train it for strength, track the weights, and let go of the mirror test.
Frequently asked questions
How do you get rid of hip dips fast?
You can't, fast or slow. Hip dips are the space between your pelvis and thigh bone, and no exercise or diet changes bone. Training grew gluteus maximus in 9 weeks in one study (Plotkin 2023), which changes the shape around the dip, not the dip itself.
Do squats get rid of hip dips?
No study shows that. In 34 untrained adults, 9 weeks of squats or hip thrusts grew gluteus maximus, but the side glutes over the dip showed little to no growth (Plotkin 2023). Squats are great for your butt. They are not a hip dip fix.
What muscle fills hip dips?
The muscles over the dip are gluteus medius and gluteus minimus, the side glutes. Hip abduction trains them through their main job (Distefano 2009). No trial has tested whether growing them makes the dip look smaller, so it is a reasonable bet, not a proven fix.
Can you get rid of hip dips at home?
The answer is the same at home and in the gym: training does not change the bone. At home you can still train the side glutes with side-lying hip abduction using ankle weights or a band, 2 sets of 15 to 20 reps per side, 2 times a week, close to failure.
Does losing weight get rid of hip dips?
Usually not. Hip and thigh fat in women tends to be slow to shrink (Manolopoulos 2010), and you cannot choose where you lose fat from. When the fat layer gets thinner, the bone shape often shows more, so the dip can look deeper.
Are hip dips normal?
Yes. They come from the normal range of pelvis and thigh bone shapes, which vary a lot between people (Carmona 2019). They are not a sign of weak glutes, poor health or bad training. Strong, lean lifters often have them.
References
- Lourenco L, Medeiros H, Ferreira L, Favoretto Dias de Oliveira N, Lopes R, Sigrist R. Hip dips technique: filling lateral depressions with hyaluronic acid of large particles. Skin Health Dis. 2024;4(6):e461. doi:10.1002/ski2.461
- Carmona M, Tzioupis C, LiArno S, Faizan A, Argenson JN, Ollivier M. Upper femur anatomy depends on age and gender: a three-dimensional computed tomography comparative bone morphometric analysis of 628 healthy patients' hips. J Arthroplasty. 2019;34(10):2487-93. doi:10.1016/j.arth.2019.05.036
- Neumann DA. Kinesiology of the hip: a focus on muscular actions. J Orthop Sports Phys Ther. 2010;40(2):82-94. doi:10.2519/jospt.2010.3025
- Flack NA, Nicholson HD, Woodley SJ. A review of the anatomy of the hip abductor muscles, gluteus medius, gluteus minimus, and tensor fascia lata. Clin Anat. 2012;25(6):697-708. doi:10.1002/ca.22004
- Plotkin DL, Rodas MA, Vigotsky AD, McIntosh MC, Breeze E, Ubrik R, et al. Hip thrust and back squat training elicit similar gluteus muscle hypertrophy and transfer similarly to the deadlift. Front Physiol. 2023;14:1279170. doi:10.3389/fphys.2023.1279170
- Rostron ZPJ, Zacharias A, Semciw AI, Kingsley M, Pizzari T, Woodley SJ, et al. Effects of a targeted resistance intervention compared to a sham intervention on gluteal muscle hypertrophy, fatty infiltration and strength in people with hip osteoarthritis: analysis of secondary outcomes from a randomised clinical trial. BMC Musculoskelet Disord. 2022;23(1):944. doi:10.1186/s12891-022-05907-4
- Dorado C, Lopez-Gordillo A, Serrano-Sanchez JA, Calbet JAL, Sanchis-Moysi J. Hypertrophy of lumbopelvic muscles in inactive women: a 36-week Pilates study. Sports Health. 2020;12(6):547-51. doi:10.1177/1941738120918381
- Distefano LJ, Blackburn JT, Marshall SW, Padua DA. Gluteal muscle activation during common therapeutic exercises. J Orthop Sports Phys Ther. 2009;39(7):532-40. doi:10.2519/jospt.2009.2796
- Wakahara T, Fukutani A, Kawakami Y, Yanai T. Nonuniform muscle hypertrophy: its relation to muscle activation in training session. Med Sci Sports Exerc. 2013;45(11):2158-65. doi:10.1249/MSS.0b013e3182995349
- Krause Neto W, Krause TLV, Gama EF. The impact of resistance training on gluteus maximus hypertrophy: a systematic review and meta-analysis. Front Physiol. 2025;16:1542334. doi:10.3389/fphys.2025.1542334
- Takahashi K, Kawama R, Wakahara T. End-divergent architecture diversifies within-muscle mechanical action in human gluteus maximus in vivo. J Biomech. 2025;179:112488. doi:10.1016/j.jbiomech.2024.112488
- Karastergiou K, Smith SR, Greenberg AS, Fried SK. Sex differences in human adipose tissues: the biology of pear shape. Biol Sex Differ. 2012;3(1):13. doi:10.1186/2042-6410-3-13
- Manolopoulos KN, Karpe F, Frayn KN. Gluteofemoral body fat as a determinant of metabolic health. Int J Obes (Lond). 2010;34(6):949-59. doi:10.1038/ijo.2009.286